
The palatine tonsils are part of the immune system and are naturally large in childhood. Two questions bring parents to the practice: very frequent tonsillitis, and tonsils so large that breathing or swallowing is obstructed. The two situations are assessed differently.
Step 1
How often is too often? Recurrent tonsillitis in children
Not every sore throat is bacterial tonsillitis; many episodes are viral and resolve without antibiotics. An episode is a sore throat confirmed by a doctor with fever above 38.3 °C, coating on the tonsils, tender neck lymph nodes or a positive strep test — not every sore throat.
What matters is the number of episodes of tonsillitis confirmed by a doctor. Tonsil removal has a clear benefit from seven episodes in the last twelve months, from five a year over two years or from three a year over three years. Below that, the course is usually observed for 6 to 12 months. The overall course is also taken into account, for example missed school days or repeated courses of antibiotics.
- Fever, sore throat, coating on the tonsils
- Swollen neck lymph nodes, difficulty swallowing
- Repeated antibiotic courses, frequent missed school days
- In children under three with fever and a sore throat, better have it checked by a doctor early
Step 2
Tonsil reduction or tonsil removal?
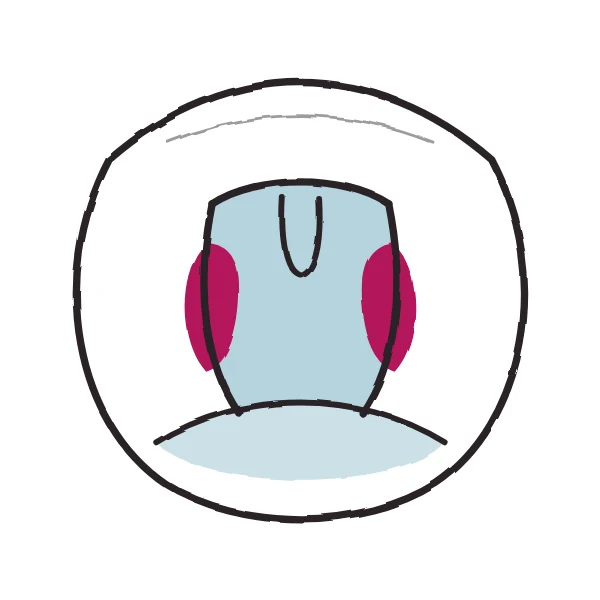
When very large tonsils with obstructed breathing, snoring or swallowing problems dominate, tonsillotomy (partial tonsil reduction) is usually considered: only the protruding part is removed and the bleeding risk is lower than after complete removal.
When very frequent, medically documented infections dominate, complete removal (tonsillectomy) is assessed. Both procedures are performed in a hospital under general anaesthesia; which route fits depends on the findings, and no particular outcome can be promised.
With frequent tonsillitis and enlarged tonsils at the same time, tonsil reduction (tonsillotomy) may also be an option. It is gentler, but the remaining tonsil tissue can become inflamed again, so complete removal is sometimes needed later after all.
Any bleeding from the mouth or nose after tonsil or adenoid surgery, even if it stops on its own, must be checked by a doctor immediately, because a small bleed can be followed by a heavier one. Go to the hospital that performed the operation or the nearest emergency department; for heavy bleeding call 144.
Step 3
What happens in the practice?
I examine the mouth, throat, nose and ears; if symptoms occur at night the adenoids (polyps) are assessed as well, since they are often involved. A hearing test or referral is arranged where needed.
We then discuss whether monitoring, conservative treatment or a hospital appointment is the appropriate next step.
Frequently asked questions
Does removing the tonsils weaken the immune system?
Immune defence is carried by a great deal of other lymphatic tissue. Current knowledge does not indicate relevant long-term immune weakness, but the indication is still assessed strictly.
Does every tonsillitis need antibiotics?
No. Antibiotics are considered only when the clinical findings support it, usually based on examination and, if needed, a swab.
How long is recovery after surgery?
After tonsillotomy it is usually a few days; after tonsillectomy considerably longer, with a bleeding risk for around two weeks. The operating hospital gives the exact instructions.
Sharing helps.
Do you know someone with similar symptoms? This page may help them.